Most important takeaways…
- Hemolysis causes roughly 40 to 70 percent of unsuitable blood specimens.
- Have patients state their name and date of birth themselves.
- Label every tube at the bedside after the draw, never before.
Practical fixes for ID, labeling, order of draw, hemolysis and reporting mistakes

Phlebotomy's biggest quality problem sits at the bedside, not the analyzer. Preanalytical errors, the work between test order and analysis, account for as much as 70 percent of laboratory errors, and most are preventable at the chair.
The fixes are unglamorous: confirm two identifiers, label at the bedside, follow the CLSI order of draw, slow down on fragile and hard sticks, protect red cells from hemolysis, and report a bad specimen instead of quietly replacing it.
None of that depends on a new device. It depends on habits, and habits get built in training and tested on every shift. Certification remains voluntary, but the habits behind it are not optional.
Most laboratory errors are made before the specimen ever reaches an analyzer. The preanalytical phase covers everything from the moment a test is ordered through patient identification, collection, labeling, handling and transport. A 2024 review places this phase at roughly 60 to 70 percent of all laboratory errors. That share is why your habits at the bedside matter more than anything downstream.
Rejection rates themselves vary widely by institution and by how each lab counts. Published 2026 studies report figures as low as 0.22 percent of samples and as high as 6.09 percent, which tells you the denominator and the definition differ from one lab to the next. What stays consistent is the short list of causes.
These are not exotic failures. Nearly every one traces back to rushing, an interruption mid-procedure, or a shortcut taken with labeling. Fixing them starts with slowing down at two points: identification and labeling.
"Are you Maria Lopez?" and "Can you tell me your name and date of birth?" sound like the same question, but only the second is real identification. A tired, anxious or confused patient will often agree to the wrong name. CLSI GP41 calls for at least two patient-specific identifiers, and the patient should state them rather than confirm ones you read out.
Accepted identifiers include full name, date of birth and medical record number. Room number, bed number and location do not qualify. Compare what the patient says with the requisition and, for inpatients, with the identification band attached to the patient. A band lying on a bedrail or bedside table cannot be relied on. Outpatients without a band should show photo ID.
Bands are not foolproof either. One 2026 figure puts their defect rate at 7.4%, which is why you check the band against the patient's own words and the paperwork instead of trusting any single source.
If the wristband, requisition and record disagree, or information is missing or illegible, stop. Do not draw. Report it to the patient's nurse or the ordering source, and let them resolve and correct the discrepancy. GP41 does not permit collecting or labeling a specimen while a discrepancy remains open. Once it is settled, document what happened, then proceed.
The temptation is practical: pre-labeling a rack of tubes before your morning run feels efficient, and it saves a few seconds per patient. That tradeoff is the single worst one in phlebotomy. A label applied away from the patient is a guess, and a guessed label is what drives wrong-blood-in-tube events, the most serious error a collector can cause.
A Pennsylvania multihospital collaborative recorded baseline mislabeling rates of 0.1 to 4.1 errors per 1,000 opportunities, then cut aggregate labeling errors by 37% over 18 months using barcode systems.2 A CDC review of 17 hospital studies found manual entry carried roughly four times the odds of patient-specimen identification errors compared with barcode systems.1 In a multicountry audit of more than 2 million blood bank samples from 20 hospitals, near-patient electronic positive patient identification was associated with a fivefold lower wrong-blood-in-tube rate.3 One 3,800-bed academic center reported a 97% relative reduction in identification errors between 2005 and 2014, though its program bundled several changes at once.
Label in the patient's presence, immediately after collection, before you leave the room or curtain. Never pre-label. Scan the wristband, scan the tube label, confirm the match on screen, then apply the label at the bedside. If the printer or scanner fails, hand-label from the requisition while still with the patient, then have a second staff member verify before the specimen leaves your hands.
A compliant label typically carries the patient's full name, a unique medical record or encounter number, the date and time of collection, and your initials or collector ID. Confirm the exact required fields against your employer's policy, since local requirements and label formats vary.
Additives can carry over on the needle from one tube into the next, so filling tubes in the wrong sequence can contaminate a specimen and skew results before it reaches the lab. The table follows the CLSI order of draw reflected in tube guides from BD Vacutainer and Greiner Bio-One. Mix each tube by gentle inversion using the count in your manufacturer's tube guide, and follow your facility's written policy, which may document exceptions such as a discard tube for butterfly draws.
| Order | Tube / Additive | Common Cap Color | Why It Matters |
|---|---|---|---|
| 1st | Blood culture (culture medium in a bottle or tube) | Aerobic bottle: blue top; anaerobic bottle: purple top | Collected first so additives from other tubes cannot contaminate it |
| Before citrate (butterfly draws only) | Discard tube (nonadditive or coagulation tube) | N/A | Clears dead space air from the winged set's tubing, which would otherwise under-fill the citrate tube |
| 2nd | Sodium citrate (coagulation) | Light blue | Needs the proper additive-to-blood ratio; with a winged set, collect a discard tube first if citrate is the first tube needed |
| 3rd | Serum: clot activator and/or gel, or a nonadditive glass or plastic tube | Red, red-speckled, or gold | Only blood cultures, glass nonadditive serum tubes, or plastic serum tubes without clot activator may be drawn before the coagulation tube |
| 4th | Heparin, with or without gel | Dark green, light green, or speckled green | Drawn after the blood culture, citrate, and serum tubes in the CLSI sequence |
| 5th | EDTA, with or without gel separator | Lavender, pearl, or pink | Drawn after heparin and before the glycolytic inhibitor tube |
| 6th | Sodium fluoride/potassium oxalate (glycolytic inhibitor) | Gray | Collected last, after blood culture, citrate, serum, heparin, and EDTA tubes |
Gentle technique and fast technique are not the same thing, and hemolysis is where the difference shows. A smooth, unhurried draw protects red cells. A forceful one ruptures them before the tube ever leaves your hand.
Wet antiseptic is another culprit. WHO guidance describes 30 seconds of application followed by 30 seconds of drying, while one tube manufacturer's poster cites 15 to 20 seconds. Either way, let the skin air-dry completely before the stick. Do not fan it, blow on it or wipe it off.
Fill every tube to its marked line. Additive tubes depend on a set blood-to-additive ratio, and coagulation tubes use 9:1 with a tolerance of about 10 percent either way.3 An underfilled citrate tube can falsely prolong PT and APTT results, which may trigger a recollection or a wrong clinical decision.1 Invert promptly after filling so the additive mixes before clots form.
Use a sterile safety lancet, preferably one that retracts automatically. After the puncture, wipe away the first drop.4 Keep the site angled downward and apply gentle, intermittent pressure around or just above it.3 Squeezing too tightly dilutes the sample with tissue fluid and causes hemolysis, so avoid milking or heavy massage.
Fill capillary tubes to the fill mark.5 With a micropipette, fill it completely with fresh whole blood, hold it at a slightly downward angle, and touch only the tip to the blood drop, never the finger.6 Wipe the outside and do not wick the open ends.
Hemolysis accounts for roughly 40 to 70 percent of all unsuitable blood specimens, according to a 2008 review by Lippi and colleagues in Clinical Chemistry and Laboratory Medicine. It matters because ruptured red cells can release potassium and other contents, making results invalid and forcing a redraw.
Adjusting your approach means changing your device, tourniquet, site and attempt limits to fit the patient in front of you. The standard adult antecubital draw does not suit every arm, and forcing it is how hematomas, hemolyzed tubes and repeat sticks happen. CLSI PRE02, the core standard for venous collection, specifically covers children and challenging patients, so treat these adjustments as part of the procedure.
WHO guidance allows capillary sampling at any age when only a small volume is needed. Accepted sites are the finger, the heel and, rarely, the earlobe. For pediatric patients:
Don't squeeze the finger or heel hard. Heavy pressure dilutes the sample with tissue fluid.
Thin skin, fragile veins and veins that roll are common. Tie the tourniquet snugly but not tightly, anchor the vein with your thumb below the site, and expect easy bruising. Avoid probing for a vein you missed. Release the tourniquet once blood flows and always within two minutes, and remove it before you withdraw the needle. Venipuncture training notes also list fragile elderly veins among the cases where capillary collection may suit a small-volume test.1
Find the vein by palpation, not by sight. A firm, bouncy vein you can feel beats a visible one you can't. A butterfly gives you more control at shallow angles. For capillary collection, training notes recommend warming the site for 3 to 5 minutes.1
Know when to stop. Training materials that cite CLSI say to hand off to a more experienced collector after two unsuccessful attempts.1 Connecticut Children's difficult-access pathway uses two attempts by any unit provider, then two by a more skilled one.2 Your facility's policy sets the actual limit.
Before you apply a tourniquet, ask about IV lines, mastectomy and dialysis fistulas or grafts. Use the other arm. If neither arm is clear, stop and follow your facility's policy or check with the nurse before you draw.
Rushing a blood draw saves a minute at the chair and can cost a second stick, a delayed result, and a clinician's trust. The fix is habit, not heroics.
What should you do if you realize a tube is mislabeled or the specimen is unusable? Stop, tell someone, and let the lab's written procedure take over. Exact steps follow your facility's policy, so learn it before you need it.
Do not relabel or "fix" a tube yourself, even if you are sure whose blood it is. Notify your supervisor or the lab as policy directs. Mislabeled or unlabeled specimens are typically rejected or canceled, and no result is reported from a specimen that cannot be identified.1 If identity cannot be verified, the patient is recollected when clinically indicated. Some hospitals make an exception for irreplaceable specimens, but only under written rules and with documentation.
Expect to record your collector ID, the reason, who was notified and when. The lab also notifies the provider or submitter.
Tell the lab, document the problem, and recollect when needed. Rejection criteria live in each lab's written procedures, and common ones include a label/order mismatch, the wrong container, insufficient volume, and clotting. Federal rules for specimen handling (42 CFR § 493.1242) expect those criteria to be defined and followed. Hospital policies such as Akron Children's Hospital's rejected specimen policy also require that the rejection reason be recorded and the submitter notified.
A near miss is an error you caught before it reached the patient or the result. Report it anyway. It shows where the process is weak. A typical incident report includes patient identifiers, times, and what the discrepancy was.1 Mislabeling is generally treated as a patient-safety event, and at least one hospital policy calls for a separate report for each specimen.2 Fields vary by institution, as there is no single universal form.
Good labs look at systems, not scapegoats. A root-cause review asks what happened, why, when, and who was involved, then examines contributing factors such as two-identifier checks, labeling steps, and barcode scanning.2 Corrective action under 42 CFR § 493.1282 is documented, and facilities commonly assign an owner, a due date, and a check on whether the fix worked. Labs may also track errors by location, collector, specimen type, and cause. CLSI standards PRE01 and PRE04 are among the references behind these practices.1
A mislabeled tube is a patient safety problem. Fixing it quietly on your own makes it worse. Work through these steps in order, and follow your facility's policy for the exact steps, forms and timelines.

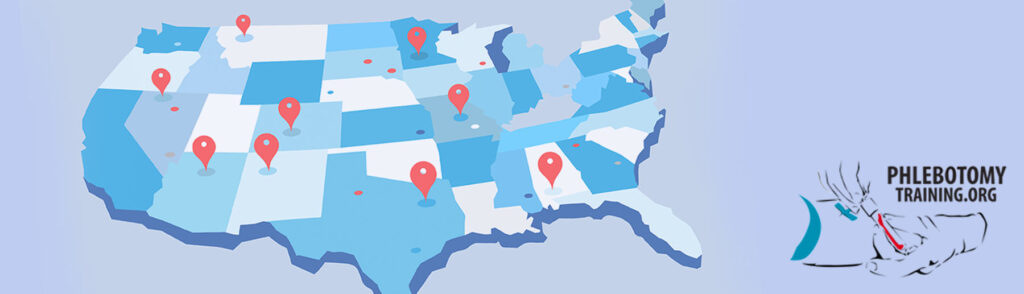
Only four states, California, Louisiana, Nevada and Washington, license phlebotomists.1 Elsewhere, certification is voluntary, but most employers expect it, and the training behind it is where error-prevention habits get built.
Most phlebotomy programs run about 4 to 16 weeks, or roughly 40 to 200 hours, through community colleges, private career schools, hospitals and blood banks. Coursework covers patient identification, order of draw, labeling and infection control. Supervised live draws then turn those rules into routine. Competency checks confirm you can repeat them correctly, not just recite them. The phlebotomy training pages on phlebotomytraining.org explain how to compare program formats and clinical components.
Exam details vary by source and change, so confirm current specs with each certifying body before you apply.
Several certifiers ask for documented live collections, so the supervised practice in your program counts twice: it builds skill and it supports eligibility.
A national certificate does not replace state authorization where it is required. California issues credentials through the Department of Public Health's Laboratory Field Services (CPT I, CPT II and Limited Phlebotomy Technician).1 Louisiana uses the State Board of Medical Examiners. Nevada uses a laboratory assistant credential through its Division of Public and Behavioral Health. Washington uses the Medical Assistant-Phlebotomist (MA-P) credential under practitioner supervision. The certification pages on phlebotomytraining.org outline how national and state requirements fit together.